Dr William Makis Ivermectin Protocol 2026 – Complete Guide + Patient Outcomes

Who is Dr. William Makis
He also shares information publicly through X.com, including anonymized patient updates, treatment progress reports, and dosing regimen discussions.
Why This Protocol Matters in 2026
Dr. Makis has treated a large volume of cancer patients using repurposed drugs since 2023. His approach centres on high-dose ivermectin combined with benzimidazoles (fenbendazole and/or mebendazole) alongside synergistic supplements and metabolic interventions. He customizes per patient, but the core protocol patterns have become increasingly consistent.This continuously updated 2026 guide compiles Dr. Makis’s latest protocols from his Substack, X posts, and patient correspondence — cross-referencing dosages, schedules, combinations, safety data, sourcing, and real patient outcomes.
Dr. Makis's Core Ivermectin Cancer Protocols 2025 - 2026
1. Standard Protocol – Most common cancers- Applicable cancers: Breast, Colon, Lung, Prostate, Melanoma, Renal, Gastric
- Ivermectin dosage: 1.0 mg/kg/day (example: 80 kg patient = 80 mg/day) – taken daily, no days off.
- Benzimidazole partner: Fenbendazole 444–1000 mg/day OR Mebendazole 1000 mg/day.
- Key add-ons: Berberine 500 mg 2–3×/day, CBD oil 100 mg/day
- Duration: Minimum 3–6 months or until NED (No Evidence of Disease)
- Applicable cancers: Lymphoma, Leukemia, Pancreatic, GBM, Sarcoma, Triple-Negative Breast, Turbo cancers*.
- Ivermectin dosage: 1.5–2.0 mg/kg/day (many patients are now on 2 mg/kg under monitoring)
- Benzimidazole partner: Fenbendazole 1000 mg/day + Mebendazole 1000–1500 mg/day (dual or triple therapy)
- Key add-ons: High-dose Berberine, DMSO topical on tumors.
- Duration: Daily until major response, then taper only after NED confirmed.
3. Low-Dose Ivermectin + High-Dose Benzimidazole Protocol
- Applicable cancers: Ovarian, Uterine, some Breast cancers (when patient cannot tolerate high dose ivermectin)
- Ivermectin dosage: 0.5–1.0 mg/kg/day
- Benzimidazole partner: Fenbendazole 1000–2222 mg/day (continuous or 3 days on/4 days off)
- Key add-ons: CBD/THC oils, Berberine, liposomal curcumin liposomal
- Duration: 6–12 months minimum
4. Maintenance / Remission Protocol
- Applicable cancers: All cancer types after achieving NED
- Ivermectin dosage: 0.5–1.0 mg/kg, 3–5 days per week only
- Benzimidazole partner: Fenbendazole 444 mg/day or Mebendazole 500 mg/day
- Key add-ons: Berberine, Vitamin D 10,000–20,000 IU, liposomal curcumin
- Duration: Indefinite or minimum 1–2 years.
Dr. Makis’s Core Protocol Rules (2025–2026)
- Take ivermectin with a fatty meal for optimal absorption.
- Use only human pharmaceutical-grade 12 mg tablets — never untested veterinary formulations.
- Monitor liver function tests (LFTs) and kidney function every 4–6 weeks throughout treatment.
- Combine with intermittent fasting or a strict ketogenic diet for potential synergistic benefit.
- Topical DMSO combined with ivermectin on accessible tumors may accelerate local response.
- Liver support: Milk thistle (silymarin) 300–600 mg/day is commonly used for liver protection and is generally compatible with this protocol.
The Ivermectin, Fenbendazole and Mebendazole Dosing
- Ivermectin — 2020: MD Anderson and Brazilian researchers published a report examining high-dose ivermectin in patients with acute myeloid leukemia, introduced 1 mg/kg/day dosage in children as young as five, with two of three children achieving temporary remission. (De Castro 2020)
- Mebendazole - 2016: Johns Hopkins introduced mebendazole at 1500 mg/day dosing (500 mg taken three times daily) in children (as young as 1 year old) with brain cancer. (Clinical Trial 2016)
- Fenbendazole - 2021: Researchers at Stanford University introduced fenbendazole at 1 gram three times weekly in 3 patients with kidney and urinary bladder cancers. (Clinical Oncology 2021)
Mebendazole vs Fenbendazole - Dr William Makis (October 2026 Update)
- Brain cancers: mebendazole preferred over fenbendazole as mebendazole can cross over the blood brain barrier.
- Brain metastasis: mebendazole preferred over fenbendazole as mebendazole can cross over the blood brain barrier.
- Adenocarcinomas (prostate, lung, pancreatic adenocarcinomas; cancers that are glandular in origin): fenbendazole is preferred.
- Squamous cell carcinomas e.g. head and neck, cervical, esophageal; mebendazole is preferred.
- The squamous vs adenocarcinoma split has no comparative trial behind it. No study has randomized or even systematically compared the two drugs by histology.
Broader Protocol Context
1. Ivermectin
- Low-grade cancers: Dose of 0.5mg/kg, 3x per week (Guzzo, et al., 2002).
- Intermediate-grade cancers: Dose of 1mg/kg, 3x per week (Guzzo, et al., 2002).
- High-grade cancers: Dose from 1 mg/kg/day (de Castro, et al., 2020) to 2 mg/kg/day (Guzzo, et al., 2002).
2. Benzimidazoles and DON*
- Low-grade cancers: Mebendazole: Dose of 200 mg/day (Dobrosotskaya, et al., 2011).
- Intermediate-grade cancers: Mebendazole: Dose of 400 mg/day (Chai, et al., 2021).
- High-grade cancers: Mebendazole dose of 1,500 mg/day (Son, et al., 2020) or Fenbendazole 1,000 mg 3x per week (Chiang, et al., 2021).
3. Intravenous Vitamin C
Intermediate- and high-grade cancers: Dose of 1.5g/kg/day, 2-3x per week (Fan, et al., 2023).Established as a non-toxic dose for cancer patients (Wang, F., et al., 2019).
4. Oral Vitamin D
All cancer grades: Dose of 50,000 IU/day for patients with a blood level ≤ 30ng/mL; 25,000 IU/day for levels 30-60ng/mL; and 5000 IU/day for levels 60-80ng/mL.Established as a non-toxic dose (Cannon, et al., 2016; Ghanaati, et al., 2020; McCullough, et al., 2019).
It is necessary to reach a blood level of 80 ng/mL of vitamin D (25-hydroxyvitamine D (25(OH) D) (Kennel, et al., 2010; Mohr, et al., 2014; Mohr, et al., 2015). This level is non-toxic (Holick, et al., 2011). Once this level is reached it must be maintained with a reduced daily dosage of ≈ 2000 IU/day (Ekwaru, et al., 2014). The vitamin D blood concentration should be measured every two weeks for high doses and monthly for lower doses.
5. Zinc
All cancer grades: Dose of 1 mg/kg/day is established as a non-toxic dose for cancer patients (Hoppe, et al., 2021; Lin, et al., 2006). The reference range for serum zinc concentration is 80 to 120 μg/dL (Mashhadi, et al., 2016; Yokokawa, et al., 2020). Once this level is reached it must be maintained with a reduced daily dosage of 5mg/day (Li, et al., 2022). The zinc blood concentration should be measured monthly.6. Dietary Interventions
All cancer grades: Ketogenic diet (low carbohydrate-high fat diet, 900 to 1500 kcal/day) (Weber, et al., 2020).Ketone metabolic therapy consists of approximately 60-80% fat, 15-25% protein and 5-10% fibrous carbohydrates. Adequate hydration and single-ingredient whole food ketogenic meals are necessary to achieve a glucose ketone index (GKI) score of 2.0 or below (Meidenbauer, et al., 2015; Seyfried, Shivane, et al., 2021). GKI should be measured 2–3 hours postprandial, twice a day if possible (Meidenbauer, et al., 2015; Seyfried, Shivane, et al., 2021).
Intermediate- and high-grade cancers: The ketogenic diet should be coupled with a water fast for 3 to 7 consecutive days in advanced cancers (Phillips, et al., 2022; Arora, et al., 2023). The water fast should be repeated several times (≈ every 3-4 weeks) throughout the treatment (Nencioni, et al., 2018), but fasting needs to be undertaken cautiously in individuals using certain drugs and those with < 20 BMI, to prevent loss of lean body mass. For patients who can not fast, the Fasting-Mimicking Diet (300 to 1,100 kcal/day of broths, soups, juices, nut bars, and herbal teas) can be used (Nencioni, et al., 2018).
7. Additional Therapeutics
All cancer grades: Moderate physical activity, 3x per week. Increased heart and respiratory rate for a period of 45 to 75 minutes (Bull, et al., 2020) with activities such as cycling, running, swimming, etc.Intermediate- and high-grade cancers or individuals who are unable to engage in physical activity: Hyperbaric oxygen therapy, 1.5 to 2.5 ATA for 45 to 60 minutes 2-3x per week (Gonzalez, et al., 2018; Poff, et al., 2015).
The protocol should be followed for an average duration of 12 weeks, regardless of cancer type. The analysis of the interactions between each of the molecules revealed no contraindications to the combination of these substances (ANSM, 2023; CRAT, 2024; Lemberg, et al., 2018; Vidal, 2024). The treatment dosage and duration can be adjusted by the physician according to the individual patient, their ability to obtain the various molecules, and the treatment results. Adaptation of the protocol to include additional molecules to restore health, could be considered by the physician. These may include: vitamin K2 (Xv, et al., 2018), vitamin E (Abraham, et al., 2019), coenzyme Q10 (Liaghat, et al., 2024), methylene blue (da Veiga Moreira, et al., 2024), niacinamide (Yousef, et al., 2022), riboflavin (Suwannasom, et al., 2020), Artemisinin + 5-aminolevulinic acid (to cause porphyrin accumulation) (Adapa, et al., 2024), melatonin (Mocayar, et al., 2020), NADH (Medjdoub, et al., 2016), and magnesium (Ashique, et al., 2023), as examples. However, antioxidant dosages should be avoided.
- Source from reputable pharmacies; avoid if pregnant or with certain contraindications.
- Evidence is anecdotal and preclinical—large trials are lacking.
- Never self treat - need medical supervision to ensure safety first.
Ivermectin vs Other Non-Conventional Cancer Treatments
Ivermectin is one of the top non-standard or non-conventional drug for cancer.A close second would be fenbendazole - which also happens to be an anti-parasitic drug that works against cancer through some difference mechanisms than ivermectin - which we cover in the article here: Fenbendazole Joe Tippens Protocol.
The Ivermectin and Mebendazole Dosing Question: What Is the Optimal Dose for Cancer? - Dr Paul Marik


 |
| Best Ivermectin Dosage for Humans with Cancer |
Ivermectin and Mebendazole Dosing Controversy - Dr William Makis
Dr. Marik’s recommendations don’t work in 95% of cancer cases. They will in 5%.
Ivermectin 12mg to 36mg doesn’t work. It’s too low. Problem is bioavailability.
Such a low dose may work in some cases of lymphoma, bladder cancer and lung cancer (with chemo). Occasionally prostate. So maybe 5% of cases.
We have used it as a MAINTENANCE Dose for Cancer prevention, not active cancer.
Mebendazole 200-400mg also doesn’t work. And it gets better.
He says there is no established dosing from Clinical Trials. Actually there is.
Johns Hopkins established 1500mg dose for children with brain cancer.
I repeat, Mebendazole 1500mg dose for CHILDREN as young as 1 years old.
Yes, CHILDREN. SEE FOR YOURSELF.
So an adult is supposed to take 1/5th the dose of a 1 year old CHILD dose that was established by Johns Hopkins Cancer Center that owns the patent on Mebendazole? REALLY???
I’m trying to be very nice here.
I’m sure Dr.Paul Marik means well and I’m sure he’s read many books and many studies. But if you don’t have the EXPERIENCE in dealing with thousands of cancer patients, you shouldn’t be giving advice. Or at least, say you are speaking “theoretically” and “hypothetically”.
Because the fact is, I have hundreds of cancer patients coming to me from “Alternative Health Practitioners” who gave low doses which did nothing and only wasted precious time the cancer patient didn’t have.
The cancer progresses on these low doses. Every single time.
Recently I had two sad cases of cancer patients who went elsewhere while we are moving to Florida, had their doses reduced (one went to a well known American Clinic, one went to a Mexican Clinic) and after a few months, they progressed.
It makes me ill.
We are testing these doses in the lab. Bioavailability is a big issue.
We are also working on better formulations of Ivermectin and Mebendazole to improve bioavailability. There are brilliant minds working on this. It can be done and it will represent the next generation of repurposed drugs.
But that’s the reason why even Johns Hopkins deemed higher doses necessary for CHILDREN as young as 1 years old, when they gave them 1500mg Mebendazole.
Dr William Makis posted a follow-up rebuttal on Substack in July 2026 (part 2). Here are excerpts from the article:
WHERE DO THE DOSES COME FROM?
MD ANDERSON (Houston, TX) & Brazilian Team introduced Ivermectin 1mg/kg/day dosing in CHILDREN with leukemia as young as 5 years old in 2020 in a small case series. Two children of three had a temporary remission (SOURCE)
JOHNS HOPKINS (Baltimore, MD) introduced Mebendazole 1500mg/day dosing in CHILDREN with Brain tumors as young as 1 year old in 2016 (SOURCE)
I just gave you the Holy Grail source of dosing for Ivermectin and Mebendazole in Cancer, approved for children from two of the largest Cancer Centers IN THE WORLD.
Is Dr.Paul Marik really telling you that an Ivermectin dose for a 5 year old child with cancer is far TOO HIGH for an adult???
Is Dr.Paul Marik really telling you that a Mebendazole dose of 1500mg for a child with cancer is far TOO HIGH for an adult and you should use 200mg instead?
ASCO Clinical Notice: Recommending Against Ivermectin and Fenbendazole for Cancer Treatment Outside Clinical Trials
The American Society of Clinical Oncology (ASCO) Clinical Notice (May 2026) takes a cautious, evidence-based position on ivermectin and fenbendazole in cancer care. ASCO strongly cautions against using either drug to treat cancer, or as an adjunct to established cancer therapies, outside the regulatory safeguards of a well-designed clinical trial.
The rationale is clear: current clinical evidence has not established that either drug provides robust benefit in treating human cancers, nor has it adequately established their safety and effectiveness in this setting. Potential toxicities and harmful interactions with other medications, including established cancer therapies, are additional concerns. ASCO therefore emphasizes the need for well-designed comparative clinical trials to determine whether either drug has a favourable benefit–risk profile and any meaningful clinical utility in oncology.
But there is an important distinction in the wording that deserves closer attention.
Does recommending against their use outside clinical trials mean recommending their use inside clinical trials?
Not exactly. The latter would imply an endorsement that ASCO has not made. However, the qualification is meaningful: ASCO is not ruling out further scientific investigation. Rather, it is saying that these drugs should not be used as cancer treatments outside the safeguards of properly designed clinical research.
When media headlines or summaries omit the words "outside of clinical trials", the apparent scope of the recommendation changes. Whether intentional or simply the result of headline compression, leaving out those qualifying words can make a conditional recommendation against unsupervised use sound like an unconditional rejection of any potential therapeutic role.
This is not quite a "neither confirm nor deny" position. ASCO has taken a firm stance against off-trial use, based on the current lack of clinical evidence and potential risks. At the same time, it recognises that properly designed clinical trials are necessary to determine whether these drugs have any therapeutic utility in oncology.
What should an oncologist say when a patient asks about these drugs?
Would an unequivocal "No, absolutely not" be consistent with the ASCO Clinical Notice?
It depends on what the oncologist means. Saying, "I do not recommend taking ivermectin or fenbendazole for cancer outside a properly supervised clinical trial" is entirely consistent with the notice.
However, dismissing the patient's question, refusing to discuss the available evidence, or declaring that further investigation is unwarranted would not reflect ASCO's recommended approach to patient communication.
In fact, ASCO specifically encourages oncologists to proactively ask patients about alternative therapies, respond with respectful curiosity, educate with empathy, maintain trust, and support shared decision-making.
The distinction matters. Patients deserve an honest discussion of both the limitations of the evidence and the reasons for clinical caution. They should not be encouraged to self-medicate, but neither should legitimate questions about emerging research be dismissed.
The bottom line: Recommending against unsupervised use outside clinical trials is not the same as declaring that these drugs have no potential worth investigating. Evidence-based medicine should be cautious about unproven treatments, but it should also remain open to well-designed scientific investigation.
Dr. Paul Marik argues in his 2026 Substack essay that relying primarily on the absence of large randomized controlled trials can provide an incomplete picture of the evidence surrounding repurposed drugs. In his view, preclinical research, mechanistic studies, pharmacologic data, observational clinical experience, and emerging real-world evidence should also be considered when assessing whether these agents warrant further investigation.
This perspective does not establish robust clinical efficacy, but it supports the argument that the evidence base should be evaluated across multiple levels of evidence rather than through randomized trials alone.Editor's Note:
From a patient's perspective, this means that participation in an appropriately designed clinical trial is the clearest pathway for investigating these drugs as cancer treatments while generating controlled evidence about their potential benefits and risks. However, clinical-trial availability, eligibility, and location can vary considerably.
What about an off-label prescription supervised by a physician? That is a separate issue from clinical-trial use and should not be confused with evidence that the treatment works. A physician may sometimes consider off-label use of an approved human drug within the applicable laws and standards of medical practice, but ASCO's current position specifically advises against using ivermectin or fenbendazole for cancer outside a well-designed clinical trial. Fenbendazole presents an additional distinction: it is a veterinary medication and has not been approved for human use.
We therefore do not recommend self-treatment. The absence of established clinical benefit does not mean that every research question surrounding these drugs has been answered; it means that the evidence is not yet sufficient to establish them as cancer treatments. Potential drug interactions, toxicity, dosing uncertainty, and interference with conventional cancer treatment also need to be considered.
Our position is that patients who are interested in ivermectin or fenbendazole should discuss the subject openly with their multi-disciplinary oncology team rather than obtaining and taking these drugs on their own. Where an appropriate clinical trial exists (below), patients can discuss eligibility with the trial investigators.
Where a patient is exploring options outside a trial, the decision should be made transparently with a qualified physician who understands the patient's cancer, current treatment, medications, and the available evidence.
The key message is simple: don't self-treat. Investigate the evidence, ask about clinical-trial opportunities, and work with a qualified physician who is willing to have an open, evidence-based discussion about potential benefits, uncertainties, risks, and alternatives.Clinical Trials
- Cedars-Sinai Medical Center (NCT05318469)
- University of Florida (NCT07487805)
- University of Miami (Shanta Dhar et al)
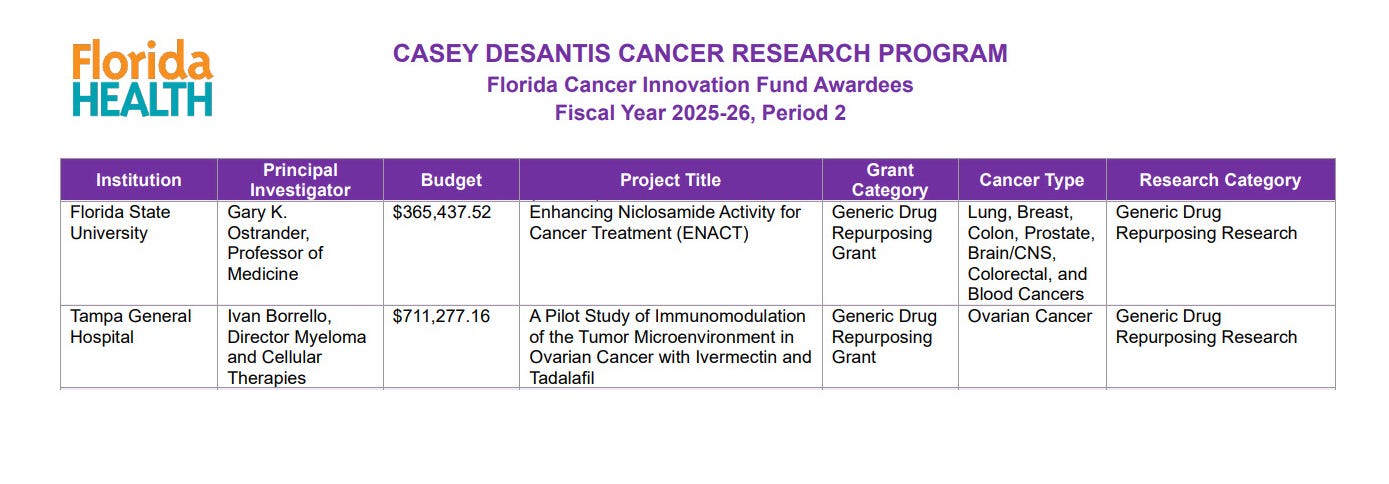
- Tampa General Hospital (Ivan Borello et al)
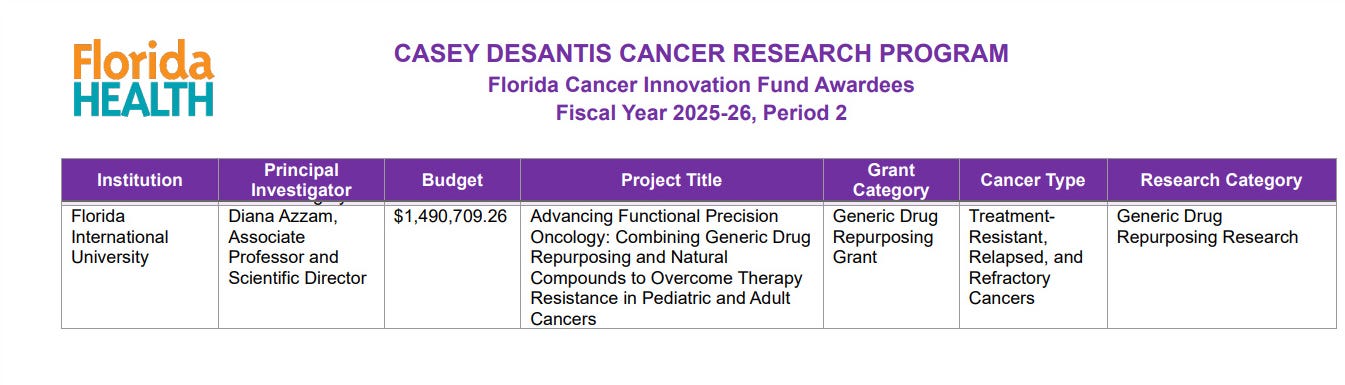
- Florida Intl University (Diana Azzam et al)
- Moffitt Cancer Center (Chang Jiang et al)
- The Cancer Care Observational Study (Dr Pierre Kory)
- Moffitt Cancer Center & Research Inst - $1.2 million
- Florida International University - $1.4 million
- Florida State University - $365k
- Tampa General Hospital - $711k
- University of Miami - $1.47 million


Should You Combine Mebendazole with Fenbendazole? 2025 - 2026 Evidence
- Preclinical: Combination index (CI) values below 1 with analogues; 80–90% xenograft reduction reported (Anticancer Research).
- Clinical Trials: Indirect—mebendazole + temozolomide (EClinicalMedicine 2022); Fenbendazole remains formally untested in RCTs.
- Real-World Cases — Dr. Makis, 100+ Stage 4 Patients:
- 100+ Stage 4 (William Makis): Pancreatic 70-87% shrink (meben AM + fenben PM); breast NED in 6 weeks (combo + ivermectin).
- Triple combination of Ivermectin, Mebendazole and Fenbendazole for Cancer: 31 Case Reports (October 2026)
- Pancreatic cancer: 70–87% shrinkage reported (mebendazole AM + fenbendazole PM schedule)
- Breast cancer: NED in 6 weeks with triple combination (ivermectin + mebendazole + fenbendazole)
- Risks: Liver strain is a known concern with benzimidazole combination therapy. Monitor weekly LFTs (liver function tests) during combination use. Also watch for gastrointestinal symptoms including nausea and elevated liver enzymes.
2026 Cohort: Ivermectin + Mebendazole Combination (197 patients)
“Despite passing a rigorous three-month peer review, the journal unilaterally retracted this study after publication, citing complaints from unnamed members of the ‘international medical community,’ while admitting there were no errors in the methodology or results. This is a primary example of medical censorship used to hide evidence that low-cost repurposed drugs have the potential to treat medical conditions like cancer.”- The Wellness Company Chief Medical Board
Hulscher et al., April 2026 — Ivermectin + Mebendazole Combination
A peer-reviewed prospective observational study evaluated 197 total patients, of whom 122 had at least 6 months of follow-up. (PubMed: May 2026)197 total patients
122 with ≥6 months follow-up
Reported Outcomes:
84.4% Clinical Benefit Rate (CBR)
32.8%: No Evidence of Disease (NED)
15.6%: Tumor regression
36.1%: Stable disease
Safety:
25.4% reported mild gastrointestinal side effects
Most patients continued treatment
Important Context:
Mixed cancer types (breast, prostate, colorectal, etc.)
Many patients also used:
Conventional treatments
Diet/lifestyle interventions
⚠️ Limitations:
Observational (not randomized)
Self-reported outcomes
Potential selection bias
No control group
Interpretation: Largest real-world dataset to date—but still hypothesis-generating.
2026 Cohort: Ivermectin Combination (146 patients)
Another related Substack review (How Ivermectin Cleared Stage-4 Cancer and Led a Daring Doctor to Treat 146 Patients), published in October 2026, describes the experiences of an anonymous physician, identified as Dr. Smith, who reportedly treated approximately 146 cancer patients using ivermectin and other repurposed medications.Its principal case concerns a 95-year-old woman diagnosed with advanced non-Hodgkin lymphoma.
According to the physician's account:
The patient had previously received chemotherapy and radiation.
She reportedly had large tumours around her jaw and collarbone.
She declined further conventional cancer treatment.
The physician introduced daily ivermectin alongside a strict ketogenic or carbohydrate-restricted diet.
Approximately three months later, a follow-up PET scan reportedly showed no evidence of cancer.
The article also describes other cases involving bladder, breast and prostate cancer.
The physician estimates that, among his 146 patients, at least 30 became cancer-free, approximately 25–30 died, and around 100 remained under treatment or follow-up.
The broader treatment approach involves combinations of ivermectin, fenbendazole and sometimes mebendazole, alongside dietary modifications.
Important qualification: These are claims and accounts reported by the original author. The article does not provide independently verifiable patient records or a controlled clinical dataset establishing that ivermectin caused the reported outcomes.
Ivermectin combined with an immune checkpoint inhibitor in advanced solid tumors
True clinical evaluations are finally catching up.
- A Phase I/II trial of ivermectin with pembrolizumab/balstilimab in metastatic triple-negative breast cancer has reported preliminary data on nine patients, and
- Researchers are also currently conducting early-phase human trials (such as the ongoing ICONIC trial scheduled through late 2027) evaluating ivermectin in combination with immune-checkpoint inhibitors for solid tumors. The randomized Phase II ICONIC trial (ivermectin plus checkpoint inhibitors, ~80 patients with solid tumors) began accruing in mid-2026 with results not expected before late 2027. Source: NCT07487805 (ICONIC), sponsored by University of Florida.
Phase 2 RCT: Mebendazole in Stage 4 Colorectal Cancer
- Overall response rate: 10% (control) vs. 65% (mebendazole group) at 12 weeks (p = 0.000)
- Progression-free survival: 3 months (control) vs. 9.25 months (mebendazole group) (p = 0.000)
Real Patient Outcomes from Dr. Makis's Practice (2025 - 2026 Cases)
- 53 year old Canadian woman – Stage 2 Triple Negative Breast Cancer (7.8 cm tumor) → Cancer Free in 7 months (Dec 2024–Jul 2025).
- 58 year old California CEO – Recurrent Stage 4 Kidney Cancer → Dying tumors in 10 weeks
- 70 year old Morocco man – Stage 4 Lymphoma → Complete remission in 2.5 months
- 39 year old Texas woman – Stage 4 Colon with liver mets → CEA from 441 → 21.9 in 4 months
- 42 year old woman – Stage 4 Kidney Cancer (lungs/liver/shoulder mets) → NED after 1 year
- 53 year old UK woman – Stage 4 Breast (12 cm tumor) → 68% shrinkage in 2 months.
- Stage 3 ovarian cancer: 12 mg daily (approx. 0.2 mg/kg for a 60 kg person) with chemotherapy led to complete resolution in 2 months.
- 83-year-old - Stage 3 follicular lymphoma: 1 mg/kg daily achieved near-total remission in 6 months.
- 54-year-old - Recurrent prostate cancer: 1.5 mg/kg daily resulted in remission in 4 months.
Frequently Asked Drug Interaction & Safety Questions
This section addresses the most frequently asked questions from patients and readers.
Can I combine this protocol with Capecitabine (Xeloda)?
Fenbendazole and mebendazole are both metabolized via CYP2C9/CYP3A4 pathways, which Capecitabine also affects. There is a theoretical drug interaction risk. No formal interaction study exists as of 2026. Patients combining these agents should disclose all medications to their oncologist, increase CBC (complete blood count) and LFT (liver function test) monitoring frequency, and proceed only under physician supervision.
What about cirrhosis or elevated liver enzymes?
High-dose ivermectin and benzimidazoles are hepatically metabolized. Patients with pre-existing liver disease (cirrhosis, hepatitis, elevated LFTs) face increased hepatotoxicity risk. If considered at all, this requires specialist supervision, lower starting doses, and more frequent LFT monitoring (every 2–4 weeks minimum).
Is ivermectin appropriate for Multiple Myeloma or Leukemia?
Dr. Makis categorizes these under Protocol 2 (Aggressive/Turbo Cancer) given their hematological nature. Some case reports suggest responses in lymphoma and leukemia. See the dedicated OneDayMD article: Ivermectin and Mebendazole in Lymphoma and Leukemia (2026) for specific case reports.
Are there negative interactions with herbal supplements?
Several supplements have been reported by patients without adverse events alongside ivermectin and fenbendazole, including liposomal Vitamin C and D, Vitamin K, Curcumin, Milk Thistle, Vitamin B complex, Turmeric, Magnesium, Krill Oil, and NAC. However, formal interaction data is lacking. Herbs that strongly inhibit or induce CYP450 enzymes (e.g., St. John’s Wort, high-dose grapefruit) may alter drug levels. Always disclose all supplements to your physician.
Does ivermectin help with parasites (non-cancer use)?
Yes — ivermectin is an approved antiparasitic for human use. For parasite treatment, dosing is typically much lower (0.2 mg/kg single dose or short course) than the cancer protocols above. Consult with a physician for appropriate dosing for your region and situation.Joe Tippens Updated Combination Protocol
- Ivermectin (25 - 50 mg/day, 6 days a week) or in the case of severe aggressive cancers up to 1mg/kg/day.
- Mebendazole (250 - 500 mg/day, 6 days a week) or Fenbendazole, commonly taken at 222 mg for six days a week, with doses increasing to up to 1 gram in cases of aggressive cancers.
- Bio-Available Curcumin (600 mg per day, 7 days a week).
- Enhanced absorption Berberine (500 mg per day, 7 days a week).
- Diet and Lifestyle:
- A 2026 study (American Association for Cancer Research), linked Ultra-Processed Foods to Reduced Survival after Cancer. Sugar, starch, saturated fat packed into ultra-processed food not only associated with obesity, diabetes, and heart disease, it also worsens cancer prognosis.
- Another 2026 study published in The BMJ examined how everyday exposure to food preservatives influences cancer risk. The findings were clear — people who consumed more preservatives had higher rates of overall cancer and breast cancer. The findings support recommendations for consumers to favour freshly made, minimally processed foods.
- Weight loss if overweight. A 2026 findings published in Nature Communications, insulin resistance has been linked to a 25% higher risk of 12 different types of cancer. Insulin resistance is often caused by obesity and its associated chronic inflammation. Both diabetes and obesity are associated with a higher risk of cancer.
- Adopt a whole-food diet and avoid ultra-processed foods, as recommended by the BMJ 2024 guidelines.
- Eliminate sugar consumption as supported by the BMJ 2023 umbrella review, which recommends reducing free and added sugars to below 25 g/day and limiting sugar-sweetened beverages to less than one serving per week to reduce adverse health effects.
- Additionally, prioritise adequate sleep and effective stress management to support overall health.
- Please note that this protocol now includes the vital Vitamin D addition, with the one day off for the fenbendazole administration. This protocol represents the most comprehensive and cutting edge repurposed drug and vitamin treatment approach to date.
- Vitamin E: Removed from the protocol (Joe Tippens, July 22, 2020) due to interactions (e.g., with blood thinners).
Where to Get Ivermectin Safely in 2026
 |
| The Wellness Company's Ivermectin and Mebendazole |
- Prescribed and supervised by licensed physicians, including consultation to determine appropriate human dosing, assess contraindications, monitor organ function, and oversee cyclic treatment regimens.
- Compounded in US-based pharmacies to pharmaceutical standards.
- Clinically tested.
- Standardized dosing (25mg ivermectin + 250mg mebendazole).
- Quality-tested for purity and consistency.
Where to buy Ivermectin and Mebendazole Compounded Formula: Available on The Wellness Company's website. Here is the link: Ivermectin and Mebendazole.
Important: Do not purchase veterinary ivermectin formulations. Concentration, inactive ingredients, and purity standards differ significantly from human pharmaceutical-grade preparations.
Conclusion
Biomarker-guided selection is feasible and underused. YAP1 expression predicted ivermectin sensitivity in gastric cancer [1], KPNB1 dependence predicted it in ovarian cancer [2], and androgen receptor positivity predicted it in prostate cancer [3]. For mebendazole, hedgehog pathway activation and c-MYB dependence are candidate selection markers [4, 5].
The approach described here is best understood as complementary to, not a replacement for, conventional oncology. Any integration of repurposed therapies should be done in genuine partnership with your healthcare team — weighing the benefit-risk ratio specific to your situation, cancer type, stage, and comorbidities.
References:
- Nambara S, Masuda T, Nishio M, Kuramitsu S, Tobo T, Ogawa Y, Hu Q, Iguchi T, Kuroda Y, Ito S, Eguchi H, Sugimachi K, Saeki H, Oki E, Maehara Y, Suzuki A, Mimori K. Antitumor effects of the antiparasitic agent ivermectin via inhibition of Yes-associated protein 1 expression in gastric cancer. Oncotarget. 2017;8(64):107666-107677. doi:10.18632/oncotarget.22587.
- Kodama M, Kodama T, Newberg JY, Katayama H, Kobayashi M, Hanash SM, Yoshihara K, Wei Z, Tien JC, Rangel R, Hashimoto K, Mabuchi S, Sawada K, Kimura T, Copeland NG, Jenkins NA. In vivo loss-of-function screens identify KPNB1 as a new druggable oncogene in epithelial ovarian cancer. Proc Natl Acad Sci U S A. 2017;114(35):E7301-E7310. doi:10.1073/pnas.1705441114.
- Lv S, Wu Z, Luo M, Zhang Y, Zhang J, Pascal LE, Wang Z, Wei Q. Integrated analysis reveals FOXA1 and Ku70/Ku80 as targets of ivermectin in prostate cancer. Cell Death Dis. 2022;13(9):754. doi:10.1038/s41419-022-05182-0.
- Larsen AR, Bai RY, Chung JH, Borodovsky A, Rudin CM, Riggins GJ, Bunz F. Repurposing the antihelmintic mebendazole as a hedgehog inhibitor. Mol Cancer Ther. 2015;14(1):3-13. doi:10.1158/1535-7163.MCT-14-0755-T.
- Walf-Vorderwülbecke V, Pearce K, Brooks T, Hubank M, van den Heuvel-Eibrink MM, Zwaan CM, Adams S, Edwards D, Bartram J, Samarasinghe S, Ancliff P, Khwaja A, Goulden N, Williams G, de Boer J, Williams O. Targeting acute myeloid leukemia by drug-induced c-MYB degradation. Leukemia. 2018;32(4):882-889. doi:10.1038/leu.2017.317.
- This content is for educational purposes only and does not constitute medical advice. Ivermectin is used off-label for cancer treatment. Always consult with a knowledgeable physician you trust.
- Statements on this website have not been evaluated by the Food and Drug Administration. The contents of this website is for educational and informational purposes only and is not intended to be a substitute for professional medical advice, diagnosis or treatment.
- The case reports presented reflect the real-life experiences and opinions of other readers or users of the website. The experiences of those readers or users are personal to those particular readers/users and may not necessarily be representative of all readers/users. We do not claim, and you should not assume, that all other readers/users will have the same experiences. Do you own research, consult with relevant medical professionals before attempting to self-treat for any condition.
- Cancer care is a team effort, with the patient at the centre of every decision. Care should be coordinated by a multidisciplinary team that may include the treating oncologist, an integrative oncologist or qualified integrative healthcare provider, family physician, nurses, dietitians, pharmacists and other allied healthcare professionals. Open communication and collaboration among all team members are essential to ensure that conventional treatments and complementary approaches are integrated safely, appropriately and effectively, with the patient’s needs, preferences and overall well-being guiding decisions.
- Considering repurposed drugs does not mean rejecting modern medicine. Rather, it may broaden the discussion of potential treatment options as part of a more comprehensive, individualised approach to cancer care. Your oncologist may be unfamiliar with certain repurposed drugs or the emerging research surrounding their use in cancer. You may therefore wish to seek a second opinion from an oncologist or qualified healthcare professional with experience in this area. Any potential use should be carefully evaluated for the strength of the evidence, possible benefits, risks, drug interactions and compatibility with your existing treatment plan. Repurposed drugs should not replace proven cancer treatments without appropriate medical guidance.
- This article is not intended to be the definitive guide, but rather a starting point on your journey toward making informed decisions and achieving the best possible outcome. It emphasizes that fenbendazole and other approaches may form part of a comprehensive, multi-modal cancer treatment strategy tailored to your individual needs. For cancer patients and caregivers, these case reports give you structure, safety checkpoints, and conversation tools you can use with your doctor. We encourage you to seek additional resources, ask questions, and explore all available options, including conventional treatments such as surgery, chemotherapy, radiation, targeted therapy, immunotherapy, and hormone therapy, as well as emerging modalities. Personalized treatment plans developed with your healthcare team offer the best chance for effective management and improved outcomes.
- Caution: Do not self-medicate without proper bloodwork and medical monitoring. Always discuss any treatment with a trusted healthcare professional. Self-medication can carry serious risks, including liver toxicity and drug interactions. For the best outcomes, any treatment should be integrated into a personalized care plan that considers the whole person—not just the disease—and includes appropriate medical supervision and ongoing monitoring.
Explore this topic with AI
Ask our research assistant questions about this article, related clinical studies, medical evidence and other OneDayMD resources.
Explore with OneDayMD AIPowered by Google Gemini Notebook · Curated OneDayMD research sources


Bonjour Dr. Makis, I would like to use Ivermectin for parasite treatment. I know these 'pesky' little parasites are hiding everywhere in our body!! What do you recommend?. I live in Montreal, Quebec, Canada. I firmly believe in the benefits of this medicine. Thank you for your reply. Colette
ReplyDeleteWhat about cirrhosis from unknown or any cause for that matter. I have not and do not drink or do drugs. I have never had hepatitis. Could low dosage Ivermectin help with this condition?
ReplyDeleteWhat are the recommendations for liver
ReplyDeleteI take milk thistle supplement for liver support as part of the ivermectin/fendendazole protocol for cancer…surprised dr. Maki’s doesn’t address this but he knows more than me…important question, good luck
DeleteDr. Makis is only on X n Substack perhaps 🤔
DeleteHow can I buy this medicine, I have colon cancer
ReplyDeleteDoes anyone know if there are any negative interactions between Fenbendazole, Ivermectin and certain medicinal herbs?
ReplyDeleteI routinely take Liposomal Vitamin D, Vitamin C, Vitamin K, curcumin, milk thistle Vitamin B complex, Tumeric, Magnesium, Krill Oil, willow bark without side effects.
DeleteI would like to know if it is good for Multiple Myeloma and Leukemia and where to get this treatment.
ReplyDeleteIvermectine febendaxole cisplatin and bevacizumab o varían cancer
ReplyDeleteIn September 2024, my mother was diagnosed with colon cancer. She underwent surgery, which was successful. However, following her diagnosis, the oncologists decided not to do chemotherapy due to her age (80), believing that cell proliferation was slow. Unfortunately, this was not the case, as a CT scan conducted one year later revealed a recurrence. Consequently, they initiated treatment with Capecitabine at a dosage of 1500 mg per day, following a regimen of two weeks on and one week off. After four months and a subsequent CT scan, her condition had not improved; in fact, it had worsened. During a meeting with the oncologists, they recommended continuing the same Capecitabine protocol without any changes to the therapy, leaving us with little hope for improvement. Despite these challenges, she remains energetic and is determined to fight. I have read that some individuals combine chemotherapy with fenbendazole and Ivermectin. Are you aware of any negative interactions between Capecitabine, fenbendazole, and Ivermectin? We would greatly appreciate any suggestions you might have. Thank you for your exceptional work.
ReplyDeleteWhat about Forcing oxidative phosphorylation by taking methylene blue very early and the antioxidant later?
ReplyDeleteMy 29 year old son was recently diagnosed with Stage III nodular melanoma. Immunotherapy infusions (2 rounds) Nivolumab and Ipilimumab. Brain is negative, 1 neck lymph node is positive. Excision and removal of lymph node is next month. I'm interested in Ivermectin beginning after excision. How do you find a doctor that is willing to monitor and perform the needed blood tests?
ReplyDeleteGreat question. My cousin has the same cancer, pretty much. I with someone would reply.
DeleteHello just curious if you’ve had any luck with this? I’m 27 and was just diagnosed with the same cancer except it’s already metastasized to other organs:|
Deletecan a pregnant woman take ivermectin for covid
ReplyDeleteI wish to take ivermectin for cancer prevention as I have strong family history of cancer and genetic mutation putting me at greater risk for cancer. What would be the general prophylaxis recommendation be for someone wishing to prevent cancer?
ReplyDeleteAnyone notice skin conditions clearing up with fenben,alien or ivermectin?
ReplyDeleteI have been following Dr Makis protocol for 10 months. My main issue is the neurotoxicity I have been experiencing. Makis disagrees with the lower dosage recommended by Marik. What to do?
ReplyDeleteI would like some help. I have just been diagnosed with a cancer on one of my ovaries, which I have had removed. I live in France and sadly my French is not fluent. My surgeon is proposing some surgery that seems to me to be extremely radical and I'm looking for an objective alternative opinion and a protocol for ivermectin etc.
ReplyDeleteThings you can do yourself: Immediately start a ketogenic diet (preferred carnivore diet 0 carb, supplement plain electrolyes 1st 30 days), then introduce 1 meal a day (intermittent fasting), lower your stress, 15-30 min light exercise like walking daily, get regular sleep 10pm-6am. Daily watch inspirational carnivore and iver fenben cancer curing videos on youtube for motivation. Listen to Dr. Thomas Seyfried.
DeleteThings with a Dr.: Meet with a Dr and get on a protocol mentioned in the articles above.
Please advise if kidney function is affected and if so is a lower dose of Fenben or Ivermectin tolerated or would a complete stop be necessary? Tippens protocol never mentioned kidney damage after continued preventative use of Fenben?
ReplyDelete…took 6 months off after 1 year of protocol and given all clear of cervical cancer, then a kidney infection must have caused some renal issues - would like to start taking 222mg of fenben 3x per week and 24mg Ivermectin 1x per week for preventative - has anyone been through reduced kidney function and continued fenben with no complications?
ReplyDelete