Fenbendazole vs Mebendazole for Cancer: What is the Difference? (August 2026 Edition)
Introduction
What is Fenbendazole used for in humans?
Fenbendazole (also known as fenben) is a veterinary medication used to treat parasites and worms such as tapeworms, hookworms, roundworms, and whipworms, in animals. It is commonly used under brand names like Panacur C and Safe-Guard.
Joe Tippens founded the protocol after he was told a story about a scientist at Merck Animal Health that had been performing cancer research on mice. The research included injecting different types of cancers into different mice body parts. The scientists discovered, through trial and error, a product in their canine product line, fenbendazole, that was batting 1.000 in killing these different cancers in the mice. The scientist was later diagnosed with stage 4 brain cancer and was given a grim prognosis of only three months to live. She decided to try the fenbendazole, and after six weeks, showed a clean scan.
Joe Tippens had been initially diagnosed with small cell lung cancer. The cancer later spread to his neck, right lung, stomach, liver, bladder, pancreas and tail bone. Like the scientist from Merk Animal Hospital, Joe was told he only had three months to live. In 2017, after hearing the story of the scientist who treated her cancer with a canine drug, Joe decided he was going to do the same. However, in addition to taking the fenbendazole, Joe added his own ingredients to the regimen (curcumin, CBD oil, and vitamin E), thus creating the Joe Tippens Cancer Protocol.
However, fenbendazole isn’t the only worming medication that has the potential to fight cancer. Researchers have also been studying how Mebendazole, a drug that can treat worms in humans, could be just as, or even more, effective at shrinking tumors and killing cancer cells.
What is Mebendazole?

“We are advocating for use of mebendazole as a therapy for those diagnosed before metastasis to see if we can slow or prevent pancreatic cancer,” Riggins says. “For those with more advanced cancers, it could be an alternative to certain surgeries. Mebendazole may have utility as a therapy after initial treatment to prevent tumor recurrence in the 15% to 20% of pancreatic adenocarcinoma patients who undergo surgery. It may also increase the durability of response to standard chemotherapy in the remaining 80% to 85% of patients with advanced disease.”
Blood-Brain Barrier Penetration: A Critical Advantage for Mebendazole
One of mebendazole’s most clinically significant properties is its ability to cross the blood-brain barrier (BBB).Bai et al. (2015) demonstrated in preclinical glioblastoma models that mebendazole achieves therapeutically effective concentrations in brain tissue and tumor. However – and this is critical – not all forms of mebendazole are equal in this regard.
Mebendazole exists in three polymorphic forms: A, B, and C. These are chemically identical but differ in their crystal structure, which affects how they dissolve, absorb, and distribute in the body.
Polymorph C reaches therapeutic concentrations in brain tissue with fewer side effects than polymorphs A or B (Bai et al., 2015). In the preclinical glioblastoma study, polymorph C significantly extended survival, and its efficacy was further enhanced when combined with elacridar (a drug that inhibits the P-glycoprotein efflux pump at the BBB).
Polymorph A showed inferior brain penetration and reduced anticancer efficacy compared to polymorph C.
Polymorph B is the least bioavailable form and is generally considered subtherapeutic for cancer applications.
This distinction matters enormously for patients, and it’s one that most online fenbendazole resources don’t address because fenbendazole doesn’t have this level of polymorphic characterization in human pharmacokinetic studies. If you’re taking mebendazole for cancer and you’re not receiving polymorph C, you may not be getting therapeutic benefit.
Mebendazole dosage for cancer treatment
Mebendazole: Key Resources
So far, several studies in the literature have used 200mg/day with some success, however given that it is safe to go up to 4g/day, when we’re dealing with aggressive cancers, 200mg/day is probably not sufficient.- 2021 Mansoori et al - For Maximum dose of 4g/day being safe, that’s from a Phase 2 Clinical Trial for Gastrointestinal Cancer.
- 2021 Chai et al - summarizes the various studies that have looked at Mebendazole in Cancer and the doses used.
- 500 mg-1500 mg/day (Phase 1 Clinical Trial, pediatric brain tumors)
- 200 mg/day (2011 Dobrosotskaya et al) (adrenocortical ca)
- 200 mg/day (2014 Nygren et al) (colon ca lung and LN mets)
- 100 mg/day (Clinical Trial, UK)
- 800 mg three times a day (phase 2 clinical trial for patients with recurrent glioblastoma) (2022 Patil et al).
- 2025 Gupta et al - This study identifies at least 7 ways that Mebendazole acts on Ovarian Cancer cells, including a brand new mechanism never before identified.
- 2025 Aliabadi et al - Critical dysregulated signaling pathways in drug resistance: highlighting the repositioning of mebendazole for cancer therapy. Front. Pharmacol. July 2025.
- 2022 Hegazy et al - Mebendazole; from an anti-parasitic drug to a promising candidate for drug repurposing in colorectal cancer (NCT03925662: Randomised Controlled Trial). Life Sci 2022.
- 2023 Mansoori S - Mebendazole enhances the anticancer effect of irinotecan and check-point inhibitor in vitro and in vivo. ESMO 2023.
- 2021 Chai et al - Albendazole vs fenbendazole for cancer? Why Mebendazole over Albendazole: “However, because of the toxicity of albendazole, for example, neutropenia due to myelosuppression, if high doses are used for a prolonged time, mebendazole is currently more popularly used than albendazole in anti-cancer clinical trials.”
- 2022 Joe et al - As a review, using a variety of in-vitro (petri dish) and in-vivo (live animal) models, Joe et al showed that mebendazole prevented the development of triple-negative breast cancer and eradicated previously established triple-negative breast cancer, and also reduced distant lung metastasis while preventing liver metastasis. Furthermore, mebendazole treatment led to a dramatic reduction in the cellular marker, Integrin β4 (ITGβ4), which is linked to the development of Cancer Stem Cells in distant locations. Even though these data were primarily animal data they would likely be applicable to humans.
- 2021 Mansoori et al (NCT03628079) - This phase 2A paper by Mansoori et al on the safety and efficacy of individualized dosed mebendazole in patients with advanced gastrointestinal cancer. The study reported that mebendazole did not help eradicate cancer in patients with various gastrointestinal cancers. The first question one has to ask is, given that the target group studied had various GI cancers, could absorption issues have contributed to the failure to find an effect? The answer appears to be YES, as the investigators observed that “Only five patients reached the target serum-mebendazole concentration.” Since there were only 10 patients in the study, and if only five had evidence that the treatment (mebendazole) was actually absorbed, it stands to reason that the study failed to find an effect because of simple absorption issues. That is, if the drug does not enter the circulatory system, it can not be expected to have an effect. This study should have never been published because of the errors in the design of the study, the low number of subjects and the glaring alternative explanation of the failure to find an effect of the drug: the subjects could not absorb the drug as evidenced by the fact that therapeutic serum levels were not reached in most subjects. But it is published and we should be aware of it. (Ben Fen 2023)
- 2019 Guerini et al - Mebendazole as a Candidate for Drug Repurposing in Oncology: An Extensive Review of Current Literature: summarized very positive preclinical data on mebendazole in treating cancers in translational studies.
- 2003 Chen et al - Precaution: Importantly, a combined use of mebendazole (>500 mg) and metronidazole (>500 mg) is prohibited because severe and rare fatal adverse events such as Stevens-Johnson syndrome (or toxic epidermal necrosis) may occur. The risk increased with increasing doses of metronidazole but not mebendazole, and there may be a synergistic interaction between mebendazole and metronidazole.
- Summary from clinicaltrials.gov:
- NCT01729260: Phase I for high-grade glioma (completed).
- NCT03925662: Phase II/III. Adjuvant for colon cancer (recruiting). (Life Sci 2022)
- NCT03628079: Phase II for GI cancers (completed). (Mansoori et al)
- NCT02644291: Phase I for recurrent pediatric brain tumors (completed).
- NCT01837862: Phase I for pediatric brain tumors (completed).

Fenbendazole vs. Mebendazole
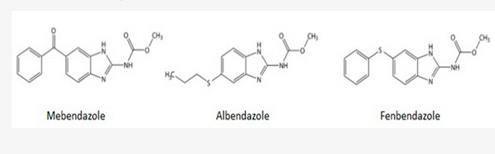
While most of the pre-clinical research uses mebendazole, probably because it is the FDA-approved-for-humans form of fenbendazole, virtually most of the self-treating clinical reports involve the use of fenbendazole.
If a patient has elevated liver enzymes, liver damage, liver metastasis, or liver diseases, it is important to work with a health professional who is familiar with the use of Fenbendazole or mebendazole and can advise whether it can be used and/or monitor lab values. A typical dose of 250mg of Fenbendazole usually does not cause side effects, but vigilance is key due to the lack of extensive studies on its effects in humans.
Evidence Level: What the Science Actually Says (April 2026 Update)
Current Consensus
-
Most evidence for ivermectin and fenbendazole/mebendazole is early clinical studies and case reports.
-
Human data remains heterogeneous.

|
| Self-reported cancer outcomes at 6-month follow-up (N=122) |
Clinical Data Snapshot
-
One positive phase 2 RCT using mebendazole in colorectal cancer (Life Sciences 2022).
-
Early-phase ivermectin + immunotherapy trials show limited but suggestive activity.
-
Case reports and anecdotal recoveries remain hypothesis-generating, not definitive (One Day MD 2026)
Bottom line: Promising—but not yet validated by large randomized trials.
2026 Real-World Observational Study: Ivermectin + Mebendazole Combination
A prospective observational study (Hulscher et al., April 2026) evaluated:
-
197 total patients
-
122 with ≥6 months follow-up
-
84.4% Clinical Benefit Rate (CBR)
32.8%: No Evidence of Disease (NED)
15.6%: Tumor regression
36.1%: Stable disease
-
25.4% reported mild gastrointestinal side effects
-
Most patients continued treatment
-
Mixed cancer types (breast, prostate, colorectal, etc.)
-
Many patients also used:
Conventional treatments
Diet/lifestyle interventions
Observational (not randomized)
Self-reported outcomes
Potential selection bias
No control group
Interpretation: One of the largest real-world dataset to date—but still hypothesis-generating.
Fenbendazole vs. Mebendazole: How the two benzimidazoles differ
Not medical advice. These tables summarise patterns from anecdotal case compilations and limited preclinical/observational data. Neither combination is FDA-approved for cancer. Veterinary fenbendazole quality varies; liver injury after self-administration has been reported. Do not delay standard oncology care.
Comparison: How mebendazole and fenbendazole differ when paired with ivermectin
| Feature | Mebendazole (human drug) | Fenbendazole (veterinary) |
|---|---|---|
| Regulatory status | Approved in humans for parasites | Not approved for humans |
| Blood–brain barrier | Better, especially polymorph C (GBM rationale) | Weaker published human PK / BBB data |
| Human dosing data | Decades of high-dose human use | Mostly extrapolated from veterinary use and anecdotes |
| Site / lab edge claimed | Brain, prostate, ovarian, some angiogenic tumours; stronger at lower doses in glioma models | High-dose pancreatic, colorectal, paraganglioma (Italian cell-line work) |
| 2026 human-form dataset | Hulscher observational cohort: compounded IVM 25 mg + MBZ 250 mg | Large social-media / Tippens-style case volume; product purity variable |
| Access / cost | Prescription or compounded | Cheap OTC veterinary product |
The 2026 Hulscher et al. observational cohort (197 patients prescribed compounded ivermectin + mebendazole, 122 with 6-month follow-up) reported an 84.4% self-reported “clinical benefit” rate (NED + regression + stable). That is not an RCT, outcomes are patient-reported, many were on concurrent standard therapy, and an expression of concern has been discussed around interpretation — but it is the largest human-formulated IVM+MBZ dataset the site leans on.
Patterns by cancer type from the case reports compilation
The main article is an index. Detailed write-ups live on linked cancer type-specific pages. Combinations are mixed; later Makis posts use IVM+MBZ more often, earlier Tippens-style stories use IVM+FBZ.Brain / glioblastoma (135 cases)
Theoretical and preclinical match favors IVM + mebendazole. MBZ crosses the BBB better and was the agent in Johns Hopkins GBM work. The site’s own comparison page says MBZ is superior at lower doses in brain-cancer cells; FBZ is “almost as good” only at high dose. Case volume is large but individual protocols on the index page are thin.Pancreatic (47 cases)
Site verdict and Italian head-to-head cell work: fenbendazole at higher dose looks stronger than MBZ. Testimonials often use IVM + high-dose FBZ (sometimes 444–1000 mg) ± other metabolic agents. Still almost all anecdotal and frequently combined with chemo.
Colorectal / appendix (85 cases)
Same site verdict as pancreas: high-dose FBZ preferred in their reading of Florio / Italian data. Separately, a small RCT of mebendazole added to bevacizumab + FOLFOX4 in metastatic CRC reported a large jump in response rate and PFS — that is the strongest conventional-trial signal for either benzimidazole, and it is MBZ, not FBZ. So the compilation’s preference (FBZ) and the only RCT signal (MBZ + chemo) point different ways.
Breast (130 cases)
Both combos appear frequently.
- IVM + FBZ often paired with CDK4/6 inhibitors or ADC (Kisqali, Enhertu) in HR+ and some TNBC stories.
- IVM + MBZ appears in several dramatic marker/scan stories (e.g. large nodal/lung volume drops in 8–10 weeks at ~1–1.5 mg/kg IVM + 1000 mg MBZ).
-
Triple IVM+FBZ+MBZ in a few aggressive TNBC cases.
TNBC stories are over-represented relative to incidence; many also used standard agents. No clean winner from the testimonials alone.
Prostate (128 cases)
Site comparison text lists prostate among cancers where mebendazole looks stronger preclinically. Testimonials use both partners. Joe Tippens–style FBZ stories exist; later high-dose IVM+MBZ stories exist. ADT and other hormone therapy are common confounders.
Lung / NSCLC (62 cases)
Historically the Joe Tippens cancer (FBZ-first). Current compilation uses IVM + either benzimidazole, sometimes triple. No consistent type-specific split.
Cholangiocarcinoma / liver (small numbered set on the index)
Both combos appear in the inline examples:
- 75-year-old man, 14 cm intrahepatic CCA: IVM + mebendazole → necrosis reported at 3 months.
- 85-year-old man, Klatskin tumor: IVM + fenbendazole + CBD → claimed complete remission at 4 months.
-
48-year-old woman, stage 4 CCA:
IVM + fenbendazole, longer-than-expected
palliative course.
Too few cases to pick a winner.
Lymphoma / leukemia
Extracted Makis posts on the index lean IVM + fenbendazole (CML, CLL, DLBCL, follicular, Hodgkin). A few add CBD or IP6. Numbers are small.
Melanoma / sarcoma / other solids
Scattered IVM+FBZ and some triple stories. No stable pattern.
Ovarian / endometrial / cervical
Site text groups MBZ with ovarian. Case counts are modest; both partners appear.Practical mapping (hypothesis only)
Hypothesis only — not a treatment protocol. Which combination the compilation + rationale lean toward:
| Cancer type | Combination the reports lean toward | Why that lean exists |
|---|---|---|
| Glioma / GBM / brain mets | Ivermectin + mebendazole | BBB penetration; Johns Hopkins GBM lineage; better low-dose activity in brain lines |
| Pancreatic | Ivermectin + high-dose fenbendazole | Site reading of Italian head-to-head cell data; many high-dose FBZ testimonials |
| Colorectal | Split signal | Anecdotes favour high-dose FBZ; the only RCT signal is mebendazole added to bevacizumab + FOLFOX4 |
| Prostate, ovarian | Ivermectin + mebendazole slightly favoured on paper | Preclinical lists on the comparison page; testimonials still mixed |
| Breast (incl. TNBC) | Either combination | Both well represented; many stories also used Kisqali, Enhertu or other standard agents |
| Lung / NSCLC | Either; historically FBZ-first | Joe Tippens origin story used FBZ; later reports use IVM + either or triple therapy |
| Cholangiocarcinoma / liver | No winner | Inline examples include both IVM+MBZ (necrosis at 3 months) and IVM+FBZ (claimed remission) |
| Lymphoma / CLL / CML | More ivermectin + fenbendazole in posted stories | Small numbers; several Makis posts used IVM+FBZ ± CBD/IP6 |
| Aggressive multi-site stage 4 | Triple IVM + FBZ + MBZ in a minority of write-ups | Used as escalation when one benzimidazole was considered insufficient — still anecdotal |
Availability often decides in practice: FBZ is cheap and OTC-vet; MBZ is a human prescription (or compounded, as in the Wellness Company product used in Hulscher).
Head-to-Head for Cancer Efficacy
2025 Head-to-Head List (Incorporating Makis/Seyfried Insights):
-
Primary Mechanism
→ Mebendazole: Tubulin/Hedgehog, anti-angiogenic (↓VEGF)
→ Fenbendazole: Glycolysis/pyroptosis, resistant cells
→ Winner: Tie—complementary (combo for mito-stem axis) -
Best Cancer Types
→ Mebendazole: Glioma (25% PFS), GI, breast
→ Fenbendazole: Breast (91% shrink), prostate, melanoma
→ Winner: Fenbendazole (metabolic turbo edge) -
2025 Case Rate
→ Mebendazole: 50%+ shrinkage (n=33)
→ Fenbendazole: 99% select (n=407)
→ Winner: Fenbendazole (anecdotal volume) -
Dosing
→ Mebendazole: 1-1.5g/day split
→ Fenbendazole: 444-1000mg 3x/week
→ Winner: Mebendazole (PK data) -
Safety/Toxicity
→ Mebendazole: Low oxidative stress
→ Fenbendazole: Liver elevation at high-dose
→ Winner: Mebendazole (FDA human) -
Cost/Access (US)
→ Mebendazole: $30-60/mo
→ Fenbendazole: $5-15/mo
→ Winner: Fenbendazole -
Synergies
→ Mebendazole: Radiation/temozolomide
→ Fenbendazole: Keto/ivermectin (Tippens)
→ Winner: Both (hybrids shine) -
Overall Score
→ Mebendazole: 90/100 (brain/trials)
→ Fenbendazole: 88/100 (affordable/resistant)
Should You Combine Mebendazole with Fenbendazole? 2025 - 2026 Evidence (Triple Therapy)
Yes, under guidance—synergy potential high.- Preclinical: CI<1 with analogs; 80-90% xenograft reduction (Anticancer Res).
- Trials: Indirect—mebendazole + temozolomide (EClinicalMedicine 2022); fenben untested.
- Cases: 100+ Stage 4 (Makis): Pancreatic 70-87% shrink (meben AM + fenben PM); breast NED in 6 weeks (combo + ivermectin).
- Risks: Liver strain; GI progression risk (CancerChoices). Monitor weekly Liver Function Tests.
Joe Tippens LiveStream, August 2026 - Joe answers your questions about his story
- I do not trust any of the other manufacturers, other than Merck. (Youtube timestamp, 3:10)
- I don't believe that anybody should be taking anything other than the powder, granules from Merck either in the brand name of Panacur C or Safeguard. (Youtube timestamp, 3:40)
- On ivermectin and fenbendazole combination, I am 90% certain is the fenbendazole doing most of the work. (Youtube timestamp, 10:50)
- Why? The one thing that fenbendazole does that none of the other anti-parasitics do, is that it attacks the down-regulators to p53. p53 protein kills cancer cells. The down-regulators are keeping the p53 levels at bay. If you can hit those down-regulators, and increase your levels of p53, I believe that the protocol is a fantastic preventative protocol for cancer. (Youtube timestamp, 11:00)
- My protocol 9 years ago was a 3 days on and 4 days off protocol, because I was worried of the potential liver side-effect. Last year, I found the research that fenbendazole can negatively affect the liver, was at 5,000 times the dosage that we recommend (222 mg/day). (Youtube timestamp, 14:25)
- If somebody is in a aggressive stage 4 cancer scenario, they should double the dose to 444 mg/day for the 1st month or so. If the liver enzymes spike, cut back the dosage. (Youtube timestamp, 16:00)
- The Korean government did a hit piece on me saying that Joe is a fraud as he was taking Keytruda (pembrolizumab) simultaneously with fenbendazole in the same period when he achieved NED (no evidence of disease). Merck did 3 different clinical trials, for Keytruda in metastatic (stage 4) small cell lung cancer (SCLC) but it failed. I'm the only survivor out of the 3 trials. In 2021, Merck went to the FDA and said "Keytruda does not work for metastatic SCLC". For NSCLC (non small cell lung cancer), Keytruda is a great drug. But in my case (SCLC), Keytruda had no impact. The wide metastasis happened after my chemo and radiotherapy. For someone with wide metastatic SCLC, I am the only data outlier in the 75 years history of MD Anderson. That was because of fenbendazole and the other things I was taking. ((Youtube timestamp, 17:00 - 22:00)
Fenbendazole vs Mebendazole in Pancreatic Cancer, Colon Cancer and Paragangliomas
VERDICT: Fenbendazole has superior cancer killing at higher doses for pancreatic cancer, colorectal cancer and paragangliomas (compared to Mebendazole and Albendazole).
Fenbendazole vs Mebendazole in Pancreatic Cancer
FENBENDAZOLE vs MEBENDAZOLE in Pancreatic Cancer - which is better? Obscure Italian study gives the answer in the battle of the anti-parasitics It's the question everyone is asking.

|
| Florio et al. Cancers 2019 |
Why We Recommend Mebendazole Over Fenbendazole (Dr Pierre Kory)
Given that benzimidazoles share a core mechanism of action, why does the specific drug choice matter? Several reasons:
1. Human Pharmacokinetic Data
Mebendazole has decades of human pharmacokinetic data from its approved use treating parasitic infections, including long-term, high-dose studies in echinococcosis patients (40–50 mg/kg/day for months to years). This gives clinicians a well-characterized safety profile with known drug interactions, metabolism pathways, and adverse effect patterns.
Fenbendazole has pharmacokinetic data primarily in veterinary species. While human case reports exist, the pharmacokinetic profile in humans is less well-defined. Dosing guidance for fenbendazole in cancer patients is largely extrapolated from veterinary data and anecdotal reports, which provides a less solid foundation for clinical decision-making. This isn’t to say fenbendazole is not safe. If you look at online discussions, many patients self administer fenbendazole without issue. However, this is not something we recommend.
2. Superior Preclinical Potency
In direct comparisons across cancer cell lines, mebendazole has consistently demonstrated greater anticancer potency than fenbendazole. In the Doudican et al. (2008) melanoma screening, mebendazole achieved IC50 values 3-4x lower than fenbendazole (0.30–0.32 µM vs. 1.2–1.4 µM). Nygren et al. (2013), screening 1,600 existing drugs against colon cancer cell lines, identified mebendazole as a top candidate from among a cluster of benzimidazoles that also included fenbendazole.
3. BBB Penetration with Characterized Polymorphism
As detailed earlier, mebendazole polymorph C has published data demonstrating brain tissue penetration at therapeutic concentrations. For patients with primary brain tumors or brain metastases, which represent a significant portion of advanced cancer cases, this is not a theoretical advantage. It is a practical one that can influence treatment outcomes.
4. Clinical Observations on Recurrence Patterns
This is where we share something that we believe patients need to hear, with the caveat that these are clinical observations, rather than published research.
Our compounding pharmacy colleagues, who have worked in the repurposed drug cancer space for nearly two decades, have tracked a concerning pattern among fenbendazole users. Many patients who took fenbendazole had excellent clinical results while on the drug. However, when cancer recurred after discontinuation, it tended to be more aggressive and significantly more resistant to treatment than would typically be expected.
We want to be transparent: this is observational data, not research. But it comes from nearly 18 years of clinical observation across a large number of patients, and we take it seriously. The pattern is consistent with what we know about cancer’s ability to adapt to selective pressures. If fenbendazole exerts a different pharmacodynamic profile than mebendazole, even subtly, it could create different resistance patterns upon discontinuation.
This observation reinforces two principles we hold firmly in our practice:
First, drug cycling matters. Cancer adapts. Any single-agent approach, no matter how effective initially, creates selective pressure that favors resistant cell populations. We rotate and cycle our protocols specifically to prevent this.
Second, these are not monotherapies. No single repurposed drug should be used in isolation. The multi-pathway, multi-drug approach is not just theoretically superior, it is clinically essential for durable outcomes.
5. Regulatory and Quality Control Considerations
Mebendazole is a human-approved pharmaceutical. When obtained from a reputable compounding pharmacy that verifies polymorph C, patients can have confidence in what they are receiving.
Fenbendazole is a veterinary product. The formulations available to consumers are manufactured to veterinary standards, which differ from pharmaceutical-grade human medications. Purity, consistency, and excipient profiles may vary. Patients self-sourcing fenbendazole from pet supply stores or online vendors have no way to verify what they’re actually getting.
Mebendazole vs Fenbendazole in treatment of Glioblastoma Brain Cancer
Mebendazole vs Fenbendazole in Osteosarcoma
What Does Science Say About How Fenben Works for Cancer?
A few studies have explored how Fenbendazole for humans can work alongside traditional cancer therapies to decrease cancer cells. For example, one study found that it may be effective in inhibiting the glucose intake of cancer cells, which could help prevent their growth and spread. Additionally, the drug has been shown to interfere with multiple cellular pathways in cancer patients, which could further impede the cancer cells’ ability to survive and replicate.The positive results of research on fenbendazole for cancer mean the drug could be repurposed for treating human ailments, including cancer. Fenbendazole for humans could save a considerable amount of time and money in developing new cancer-fighting drugs.
Is Fenbendazole Safe for Humans?
Fenbendazole for humans is considered safe because of its low toxicity and high safety margin, as indicated by limited studies. However, it is important to remember that the FDA has not approved it. To determine the proper dosage of Fenbendazole for humans, studies have shown that a single oral dose of up to 2,000 mg per person or multiple doses of 500 mg per person for 10 days are generally safe. It’s important to note that these are only general guidelines, and the appropriate dosage may vary depending on each person’s specific cancer.
According to the product description on Amazon, fenbendazole
is "Safe for all Dogs 6 weeks and older, including pregnant
Dogs".
Based on toxicology studies, benzimidazoles such as
Fenbendazole, Mebendazole or Albendazole seem to be safe
drugs.
However, a drug without any side-effects does
not exist. Scientific data reports do not reveal significant
adverse reactions from taking fenbendazole. Despite the fact,
there are anecdotal reports of potential toxicity: Up to 5 % of
people can experience stomach discomfort or diarrhea when taking
large quantities of fenbendazole with no breaks.
People with severe liver or kidney failure have lower medication
excretion rates, therefore, fenbendazole can accumulate and
cause unexpected side-effects. Doses should be divided
accordingly in this situation.
When used in large
quantities for a long period of time without breaks,
fenbendazole can cause an asymptomatic liver enzyme increase due
to the fact of the substance being mainly metabolized in the
liver. This is reversible with the help of a couple week pause
from the medication.
Therefore, patients should get a blood panel that includes the
liver enzymes of AST, ALT, Alkaline Phosphatase, before taking
Fenbendazole. Liver enzymes may also be elevated from cancer
treatments, alcohol use, certain medications, and cancer
itself.
Elevated liver enzymes indicate a liver that
is stressed and inflamed, and adding to its burden with
Fenbendazole would not be recommended.
Generally, for those with normal lab values, after one month of
Fenbendazole treatment, patients should get a comprehensive
metabolic panel (CMP). This standard blood test will check the
liver and kidney function to assure that the patient is
tolerating Fenbendazole without any concerning impacts on the
vital organs.
The protocol was designed to keep the
liver in optimal health, therefore the schedule of weekly 3 days
on, 4 days off was previously suggested. However, more and more
people are using fenbendazole on a daily basis without problems.
Safety & Side Effects: Mebendazole vs Fenbendazole
For platelets, thrombocytopenia is not nearly as well established or prominent an adverse effect of mebendazole as neutropenia. The current label specifically lists neutropenia/agranulocytosis rather than thrombocytopenia. Nevertheless, high-dose/prolonged exposure can occasionally produce more generalized marrow toxicity, so a falling platelet count should not automatically be assumed unrelated.
Fenbendazole is much more uncertain. It is a veterinary benzimidazole and lacks adequate controlled human safety studies, particularly with chronic dosing. Therefore, we cannot reliably quantify its effects on human neutrophils or platelets or assume that its hematologic safety profile is identical to mebendazole.
Fenben vs Fenbendazole: What's the Difference?
Yes, Fenben is the brand name for the active ingredient fenbendazole (source). Dewormers, such as Fenben and fenbendazole, play a crucial role in keeping livestock healthy. Many wonder if these terms refer to different products or are interconnected. The truth is that Fenben is not merely another name for fenbendazole but rather a brand that harnesses the active ingredient fenbendazole to combat parasitic infestations in animals.Key Takeaways: What This Means for Cancer Patients
The science behind benzimidazoles as anticancer agents is real. The mechanisms are well-characterized, the preclinical data is extensive, and the emerging clinical evidence is encouraging.Mebendazole is the superior clinical choice within this drug class for human cancer patients. This statement is based on potency data, human pharmacokinetic characterization, polymorph-specific brain penetration research, and 18 years of clinical observations from compounding pharmacy colleagues.
No benzimidazole should be used as a monotherapy. Cancer adapts. Multi-pathway coverage – using benzimidazoles alongside ivermectin, metabolic interventions, and other repurposed agents – provides the best chance at durable outcomes.
Protocol cycling management matter. The same adaptability that makes cancer deadly also means static, unchanging drug regimens lose effectiveness over time.
Clinical supervision is essential. Drug interactions, polymorph verification, dosing optimization, monitoring, and integration with conventional treatment all require experienced clinical management.
Primary Source and Reference:
https://healnavigator.com/blog/fenbendazole-for-humans-vs-mebendazole/
- Please do not consider this guide as personal medical advice, but as a recommendation for use by professional providers. Consult with your doctor and discuss with her/him.
- As we do not have information about you, our aim here isn't to replace your doctors' advice. It is intended as a sharing of knowledge and information. Do take note that most treatments are not 100% protective or curative against cancer. It's a continuous struggle between the immune system and the cancer cells. Cancer treatments are meant to assist the immune system in this battle.
- Cancer treatment should be part of a multi-modal approach in order to provide the best possible outcome. Diet and lifestyle changes are meant to run alongside conventional treatment. They are complementary, not alternative.
New & Improved Joe Tippens Protocol
- Ivermectin (25 mg/day, 6 days a week) or in the case of severe aggressive cancers up to 1mg/kg/day (6 days a week).
- Mebendazole (250 - 500 mg/day, 6 days a week) or Fenbendazole, commonly taken at 300 mg for six days a week, with doses increasing to up to 1 gram in cases of aggressive cancers.
- Vitamin D (62.5 mcg [2500 IU] seven days a week).
- Bio-Available Curcumin (600 mg per day, 7 days a week).
- Enhanced absorption Berberine (500 mg per day) to starve your cancer of sugar.
- Diet and Lifestyle: Eliminate sugar consumption as supported by the BMJ 2023 umbrella review, which recommends reducing free and added sugars to below 25 g/day and limiting sugar-sweetened beverages to less than one serving per week to reduce adverse health effects. Adopt a whole-food diet and avoid ultra-processed foods, as recommended by the BMJ 2024 guidelines. Additionally, prioritise adequate quality sleep and effective stress management to support overall health.
- Please note that this protocol now includes the vital Vitamin D addition, with the one day off for the fenbendazole administration. This protocol represents the most comprehensive and cutting edge repurposed drug and vitamin treatment approach to date.
- If you are taking ivermectin and mebendazole, you might not need fenbendazole. Consult your doctor.
- Vitamin E: Removed from the protocol (Joe Tippens, July 22, 2020) due to interactions (e.g., with blood thinners).
Related:

Researched and approved by Dr. Peter McCullough.
- Prescribed by licensed medical professionals
- Compounded and dispensed by a licensed US-based pharmacy
- Approved for human use


the ingredients for humans and animals is same but in different forms right so should be equal just like ivermectin is same but much cheaper if get it from the tractor supply
ReplyDeleteI agree totally with the above....it's all about money, people........
DeleteWith the advertised Ivermectin and mebendazole compound, why is the one day off per week not necessary for the mebendazole as it was for the fenbendazole in the Tippens Protocol?
ReplyDelete